ENDODONTICS AND ESTHETIC DENTISTRY
ENDODONTICS AND ESTHETIC DENTISTRY – Noah Chivian, DDS, Donald E. Arens, DDS, MSD, Asgeir Sigurdsson, cand. odont., MS
Part of the success of esthetic dentistry depends on the dentist’s ability to use teeth that have pulps compromised by trauma or injury. The role of the endodontist or general dentist performing endodontic procedures is to clearly intercept or eliminate the potential for problems. An equally important role is to respond to pulpal disease after esthetic restorations have been completed.
Endodontics has clearly established its role in providing the foundation needed to rebuild the dentition to form, function, health, and esthetics. As long as there is sufficient tooth structure to restore and a healthy periodontal complex for support, root canal therapy is the treatment of choice when a pulp is diseased or compromised by restorative demands. Although regional differences in techniques and materials exist, there is general agreement within the endodontic community on principles, that is, strict adherence to the endodontic triad of microbial disinfection and control, debridement, and the sealing of the canal system. With proven and predictable success rates, dentists can include endodontically treated teeth in their esthetic restorative treatment plans with the utmost degree of confidence.
Endodontics should be incorporated into the multidisciplined treatment process when the ultimate esthetic design is being determined. Treatment sequencing can be established and painful episodes and disruption of the restorative schedule avoided if the pulpal health and any previously root canal-treated teeth are evaluated early in the planning stages. The patient should be informed that the overall treatment plan is dynamic and may change as conditions arise. It is equally important to evaluate the patient’s radiographs, and if deep existing amalgam or other restorations will be redone as part of the treatment plan, the patient should be advised of future problems owing to the depth of those restorations. If, at a later time, there are complications such as an inflamed pulp or pain following final cementation, the patient has at least been forewarned. This problem is sometimes complicated by difficulty in seeing the depth of certain tooth-colored restorations.
The removal of existing restorations, excavation of decay, and paralleling of multiple abutments may require periodic reassessment and endodontic reconsideration. Sensitive teeth that do not respond to palliative measures within a reasonable period of time may require pulpectomy. There is nothing more disheartening to a patient who has completed 18 months of combined orthodontic, periodontic, and restorative treatment than to experience a “toothache” shortly after final cementation. Although pulpal problems cannot always be predicted, a great majority can be avoided with insight, careful evaluation, and good judgment.
The success of any reconstructive treatment plan depends on the health of the pulp, the periradicular area, and/or the quality of the existing root canal therapy of the teeth to be restored. In an effort to determine this condition, a standardized evaluating procedure should include the following:
• Communication that includes listening and recording
• Visual examination
• Periodontal probing
• Thermal tests
• Electric tests
• Cavity tests
• Periapical tests
• Percussion
• Palpation
• Bite tests
• Radiographic evaluation
Besides knowing the medical condition of the patient, the diagnostician should ask the patient about past dental experiences. Their desires and objectives should be clearly defined. If neglect is evident, the reasons for the neglect should be determined and discussed. If phobia and anxieties exist, the extensiveness of the case should be explained and relaxation techniques should be offered to ensure a comfortable and pain-free treatment experience. In addition, when a professional air of confidence, concern, and care is exhibited by the doctor, the patient’s faith and interest can be gained. Once this rapport is established, the patient becomes far more receptive to accepting and entering a treatment program regardless of its difficulty and their apprehensions. The quality of treatment is inversely proportional to the level of stress experienced by the patient and the doctor during the procedure. Again, warning your patient about the potential for existing restorations to require future endodontic treatment is vital for continued patient trust.
Listen, Learn, and Record. Dentists are the professionals who must perform the tests, interpret the results, and design a treatment based on the information gathered. When the diagnosis is not evident, the dentist must turn to the patient for that one pinpointing clue. Sir William Osler, the famous English physician, once said, “Listen, listen, listen — for the patient is giving you the diagnosis.” This statement is profound. The diagnostician must not only ask sufficient and leading questions to obtain as much information as possible but must also listen carefully to interpret the verbal response and its expressed meaning. Patients should be quoted verbatim in the chart, and their answers must become a permanent record for review.
Direct examination of each tooth with some method of magnification (loupes or a microscope) is essential to locate fracture lines, decay, or defective restorations.
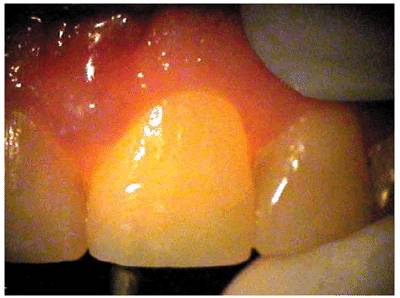
Transillumination via a fiber-optic light may be of great assistance in detecting color shifts in a crown (Figures 19-1A, and 19-1B). A tooth with a pink or reddish hue would more than likely indicate internal hemorrhage from a recent injury (Figure 19-2), a dental procedure (Figure 19-3), or gingival tissue hyperplasia that has invaded a coronal cavity produced by caries or resorption (Figures 19-4A, 19-4B, 19-4C, and 19-4D).
A gray, blue, or black color might indicate blood infiltrate hemostasis within the dentinal tubules and chamber, long-term necrotic tissue (Figure 19-5), or silver precipitants from certain root canal sealers and filling materials (Figures 19-6A, 19-6B, and 19-6C). A yellow or brown (Figures 19-7A, and 19-7B) unrestored crown often represents a physiologically calcified nonpathologic obliteration of the root chamber/ canal. Pharmacologically affected (ie, tetracycline-stained) teeth may vary in color from yellow to black (Figures 19-8A to C), and their drug fluorescence and etiology may be verified by using an ultraviolet or Woods black light.
The reader is referred to the chapter on bleaching as many of these discolorations can be reduced or eliminated by oxidizing techniques and agents without requiring endodontic intervention.
Teeth with vertical fractures have a diagnostic constant. The transilluminated light does not pass through the fracture line, but the crown beyond the fracture (Figures 19-9A and B) or the opposite cusp(s) (Figure 19-10) appears darker. Periodontal probing, cold testing, and a bite test will possibly assist in confirming the diagnosis of cracked tooth syndrome.
Figure 19-1A: Transillumination of a maxillary left central incisor with a necrotic pulp.
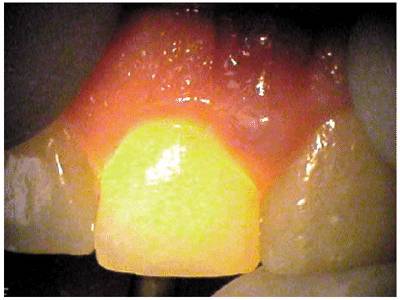
Figure 19-1B: Transillumination of the adjacent tooth with a vital pulp. Because there is active blood flow through the live pulp tissue, the tooth appears brighter to the fiber-optic light than the adjacent tooth with a necrotic pulp.
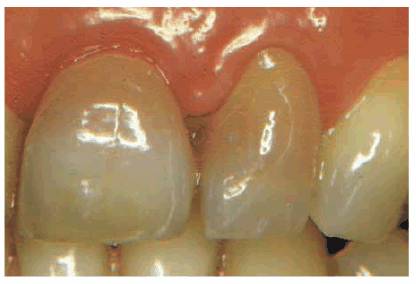
Figure 19-2: The maxillary central and lateral incisor teeth experienced a concussion injury and there was subsequent extravasation of blood causing the reddish hue.
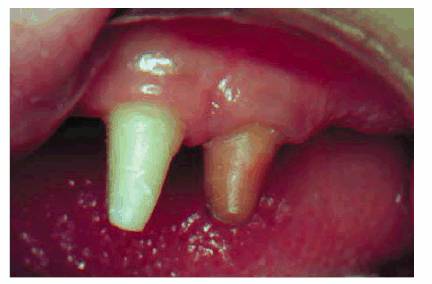
Figure 19-3: One week following crown preparation, the tooth structure was red, signifying extravasation of blood and the need for pulp extirpation.
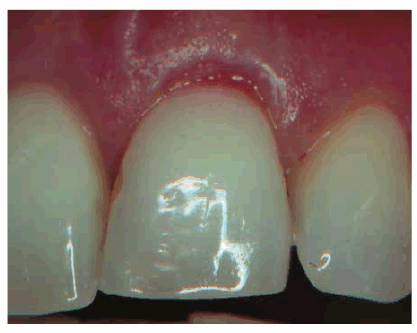
Figure 19-4A: Pink spot as a result of external resorption.
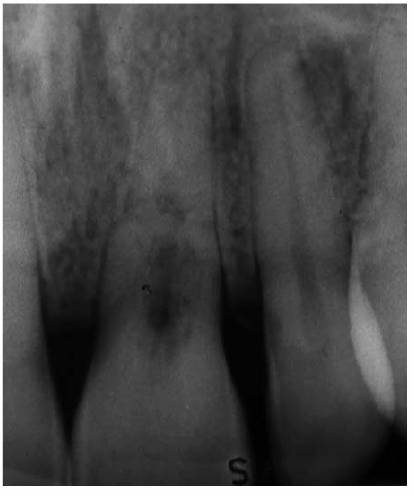
Figure 19-4B: Radiograph of the same tooth showing external resorption.
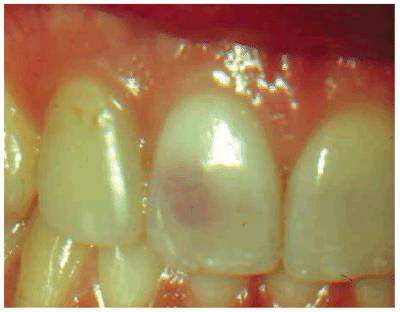
Figure 19-4C: Pink spot as a result of internal resorption.
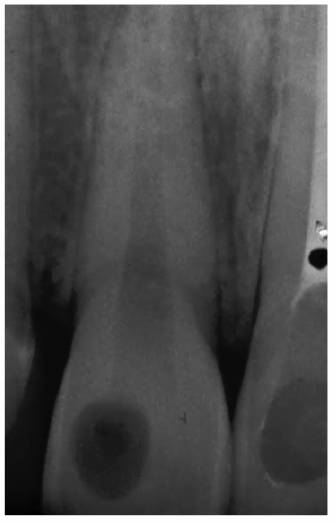
Figure 19-4D: Radiograph of the same tooth showing internal resorption.
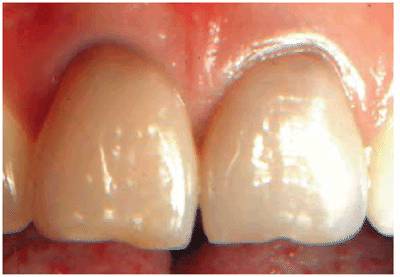
Figure 19-5: Discolored maxillary central incisors with necrotic pulps.
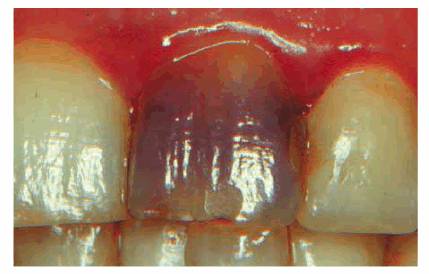
Figure 19-6A: Discoloration from silver-containing root canal cement.
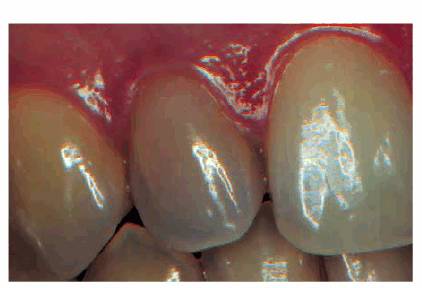
Figure 19-6B: Gray color of crown from a post.
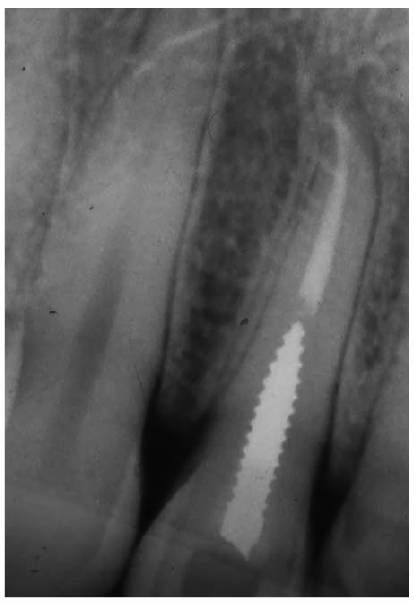
Figure 19-6C: Same radiograph as 19-6B. An unnecessary post that caused the discoloration.
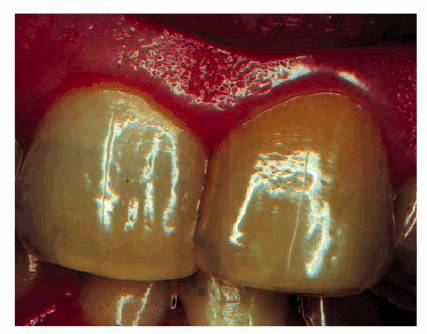
Figure 19-7A: The crown of this maxillary central incisor discolored gradually over a 3-year period following a concussion injury. The complete fill-in of the pulp chamber with dentin is the cause of the yellowish brown hue. In the absence of periapical radiographic changes and clinical symptoms, endodontic therapy is not indicated.
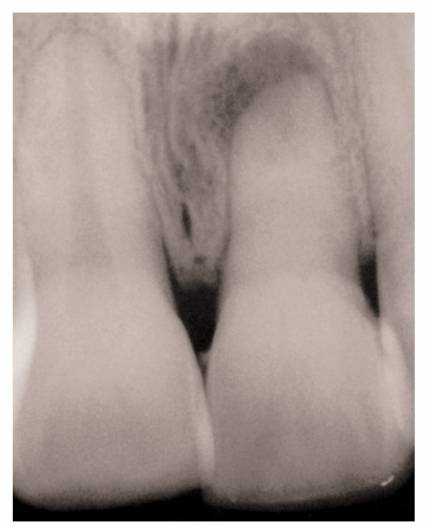
Figure 19-7B: Radiograph of a similar maxillary central incisor 10 years after a concussion injury. The pulp chamber is filled in with dentin producing the discoloration. In this case, there was pulp death years after the discoloration appeared. Because the pulp canal was obliterated, a surgical approach was used to seal the apex.
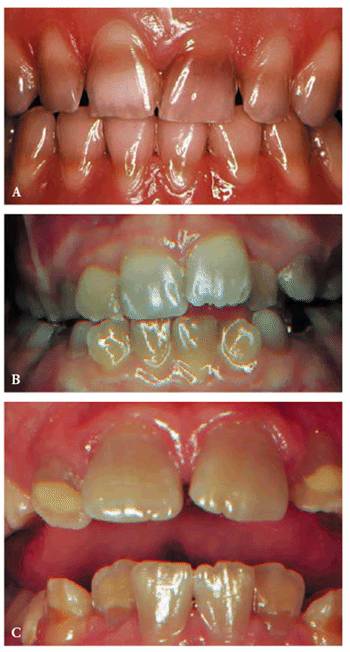
Figure 19-8A to C: (A) Brown staining from Terramycin. (B) Gray staining from Acromycin. (C) Tan staining from Aureomycin.
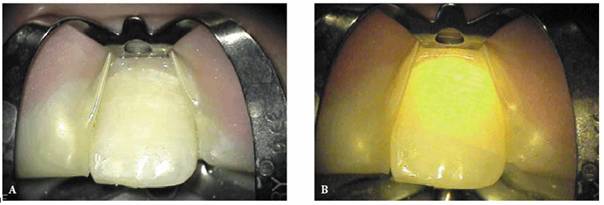
Figure 19-9A and B: (A) View of a maxillary central incisor tooth with overhead lighting. No fracture is visible. (B) Transilluminated view of the same tooth revealing the fracture line.
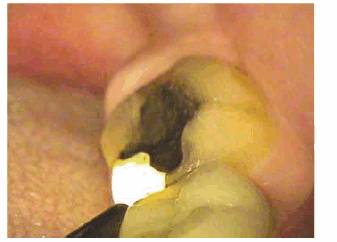
Figure 19-10: Transillumination of a mandibular second molar. The fracture lines at the mesial and lingual grooves do not allow the light to pass through.
[NextPage]
Periodontal Probing
The depth of the sulcus and individual pockets are of concern to the treating dentist or endodontist. There are two main reasons for that concern. One is that if there is a combined periodontal endodontic problem associated with a tooth, the true cause of the problem is not only difficult to diagnose but could also be even more difficult to manage during treatment. The second issue is that if there is an isolated, narrow, but deep periodontal pocket somewhere around the tooth, a vertical root fracture has to be ruled out prior to any further restorative treatment. The pocket could be just a draining sinus tract from a necrotic and infected pulp. Endodontic therapy would then be indicated, and the pocket should heal without any periodontal therapy within days after the initial endodontic visit. The pocket could also be associated with a vertical root fracture, and if that is the case, the prognosis of the tooth is hopeless. Endodontic therapy would not clear up the pocket, nor would periodontal therapy. Extraction of the tooth or removal of the root would be the only treatment option.
In an effort to determine the vitality of a pulp, the cold test is probably the most commonly advocated. In the past, an “ice pencil” (water frozen in sterilized anesthetic cartridge and removed) (Figure 19-11) or an ice cube was the only consistent way to chill a tooth. But there are several problems with using frozen water: it is not very cold, so the stimulus may not be intense enough to penetrate through a porcelain crown, and cold water from the pencil could leak on adjacent teeth or gingival tissue, giving a false impression of pulpal vitality in the tooth that is being tested. However, in a tooth with an acute pulpitis, an ice pencil is an effective diagnostic tool. Recently, 1,1,1,2-tetrafluoroethane has become available in spray form (Endo-Ice, Hygenic, Akron, OH) (Figure 19-12). This gas is relatively cold (-26°C), enough to penetrate through most crowns, and more importantly, the ice crystals will not turn into liquid prior to evaporating; rather, they will rapidly turn into gas on the tooth’s surface. The use of this system is simple and inexpensive, the gas is sprayed on a cotton applicator, 14214w227o and then the chilled cotton is placed on the tooth that is to be tested.
Dry ice cylinders (Odontotest Thermal Pulp Tester, Miltex, York, PA) are also a very good way to investigate pulpal response to cold. Carbon dioxide is very cold (-70°C), so it will penetrate most if not all restorations, and like tetrafluoroethane, it will evaporate without turning into liquid on the tooth. There was some concern initially that the extreme cold would be dangerous to pulp, dentin, and/or the enamel, but in a series of studies by Peters et al.23 and Ingram et al.,13 they demonstrated that it did not do any damage to any structures investigated.13
The response of a normal, healthy, vital pulp is sharp and quickly dissipates once the stimulus is removed. If the response is quicker, more intense, and prolonged, it usually indicates an irreversible pulpitis. When calcified pulp chambers or constricted canals exist, the response from an otherwise healthy tooth may be delayed or nonexistent. The reduced conductivity can mislead the operator. Therefore, other tests must be used to confirm negative responses.
When faced with teeth that are heavily restored, the final tests can be delayed until the tooth has been excavated, and the patient is in a provisional restoration. By wisely testing prior to final cementation, the true status of the pulp may be validated, and any changes that may have arisen during the fabrication interval can be appraised.
Heat is the least informative of the pulp tests and the most difficult to apply. Heated water applied to an individual tooth after it has been carefully isolated by a rubber dam is the most reliable method, but it is time consuming, and extreme care has to be taken so that there is no leaking under the rubber dam. It is recommended to start isolating and stimulating a tooth that is posterior to the one that is suspected to be heat sensitive and then move the rubber dam anteriorly tooth by tooth so that if there is a leak under the rubber dam, it will leak only on an already tested tooth. Heated temporary gutta-percha stopping applied to the lateral surface of a natural tooth or a metal surface of a veneer casting has been recommended, but it is difficult to control the heat, and the stopping has the tendency to stick on the tooth, causing prolonged stimuli. A rubber polishing wheel in a low-speed handpiece is an alternative also, but because it is difficult if not impossible to control the stimulus, this method is not recommended. The antiquated method of touching a tooth with a red hot burnisher should be avoided because of the risk of overheating the tooth and pulp, and there is no control over how intense the stimulus will be.
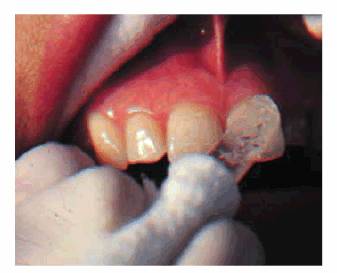
Figure 19-11: An ice pencil being applied to a maxillary central incisor tooth.

<p align="center" class="MsoNormal" style="text-align: ce